Ventilation and lung volumesSpec B3.1.5, B3.1.6
In short
Ventilation is the movement of air into and out of the lungs, caused by pressure changes in the thorax. Contraction of the diaphragm and external intercostal muscles raises thorax volume so pressure falls and air flows in. Tidal volume, vital capacity and the inspiratory and expiratory reserves are measured with a spirometer.
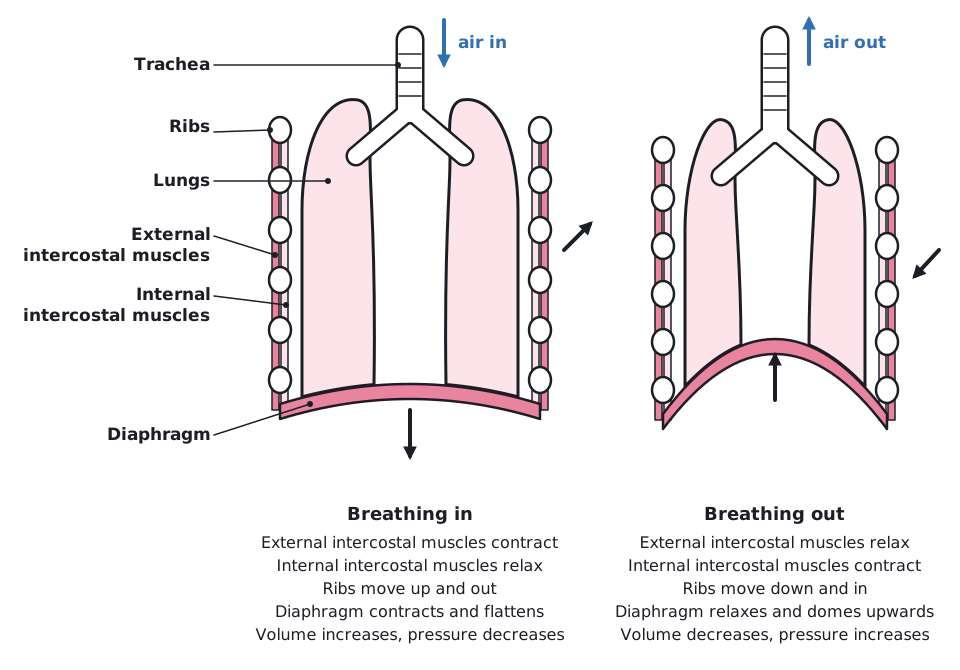
Air always flows from higher to lower pressure. Muscles change the volume of the thorax, which changes the pressure inside it (pressure and volume are inversely related).
 (opens full size in a new tab)
| Structure | Inspiration (breathing in) | Expiration (breathing out) |
|---|---|---|
| Diaphragm | Contracts and flattens, moving down | Relaxes and is pushed back up into a dome (by elastic recoil and the abdominal organs; in forced expiration also by the abdominal muscles) |
| External intercostal muscles | Contract, pulling the ribcage up and out | Relax |
| Internal intercostal muscles | Relax | Relaxed in quiet expiration; contract in forced expiration, pulling the ribcage down and in |
| Abdominal muscles | Relax, so abdominal organs can be pushed down | Relaxed in quiet expiration; contract in forced expiration, pushing abdominal organs and the diaphragm up |
| Ribs | Move up and out | Move down and in (by gravity and elastic recoil in quiet expiration; pulled by the internal intercostals in forced expiration) |
| Thorax volume and pressure | Volume increases, pressure falls below atmospheric, air flows in | Volume decreases, pressure rises above atmospheric, air flows out |
Quiet expiration (breathing out at rest) is mainly passive: the diaphragm and external intercostal muscles relax, and the stretched lungs and chest wall recoil elastically, so thorax volume falls. Forced expiration (during exercise, coughing, or when measuring vital capacity or expiratory reserve) is active: the internal intercostal muscles and the abdominal muscles contract, so more air is pushed out, faster.
Do not say the internal intercostal muscles contract in every breath out. They contract only in forced expiration; quiet expiration relies on muscle relaxation and elastic recoil.
Lung volumes
- Tidal volume
- The volume of air breathed in or out in one normal breath.
- Inspiratory reserve volume
- The extra volume of air that can be breathed in by force after a normal inspiration.
- Expiratory reserve volume
- The extra volume of air that can be breathed out by force after a normal expiration.
- Vital capacity
- The largest volume of air that can be breathed out after the deepest possible breath in: tidal volume + inspiratory reserve + expiratory reserve.
Some air always stays in the lungs (the residual volume), so a spirometer cannot measure it and vital capacity is less than total lung volume.
Measure lung volumes with a digital spirometer, or by breathing out through a tube into an upturned, water-filled, calibrated bottle and reading the volume of water displaced. Repeat each measurement three times and use the mean.
Reading a spirometer trace
On a spirometer trace, a normal breath goes from 2.3 dm³ to 2.8 dm³. The deepest breath in reaches 5.8 dm³ and the deepest breath out falls to 1.2 dm³. Find the tidal volume, inspiratory reserve, expiratory reserve and vital capacity. (Practice data.)
- Tidal volume = 2.8 − 2.3 = 0.5 dm³
- Inspiratory reserve = 5.8 − 2.8 = 3.0 dm³
- Expiratory reserve = 2.3 − 1.2 = 1.1 dm³
- Vital capacity = 5.8 − 1.2 = 4.6 dm³ (check: 0.5 + 3.0 + 1.1 = 4.6 dm³)
Answer: TV 0.5 dm³, IRV 3.0 dm³, ERV 1.1 dm³, VC 4.6 dm³
Written and checked against the IB Biology HL specification · Updated October 2026